
Share
Gut Health
Men's Health
Women's Health
Emulsifiers and your gut: What the new human trial actually found
5 min read

Key takeaways
- A 2026 placebo-controlled human trial found lower fecal short-chain fatty acids with emulsifier exposure.
- The trial did not find a parallel increase in major intestinal or systemic inflammatory markers.
- Different emulsifiers produced different signals, so treating them as one identical category oversimplifies the data.
- The practical move is reducing overall dependence on highly processed foods, not building a panic-driven ingredient blacklist.
The emulsifier story just got more complicated
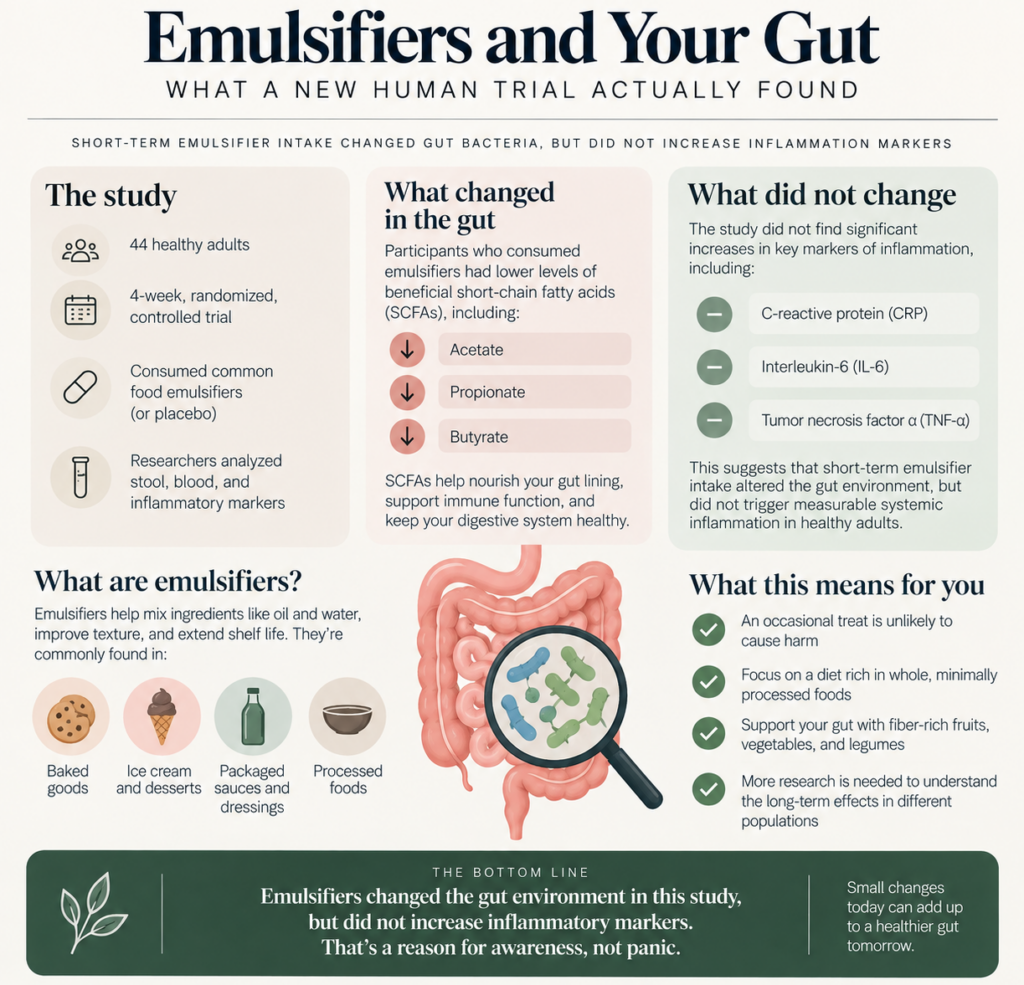
Emulsifiers are the ingredients that keep salad dressing smooth, ice cream creamy, and packaged foods from separating on the shelf. For years, much of the concern about them came from animal and laboratory research. A 2026 placebo-controlled human trial finally tested five common emulsifiers under controlled dietary conditions.
Sixty healthy adults first followed an emulsifier-free diet for two weeks. They then continued that diet while receiving carboxymethyl cellulose, polysorbate-80, carrageenan, soy lecithin, native rice starch, or no additive for four weeks. The headline result was not a burst of inflammation. It was a shift in gut metabolites.
The short-chain fatty acid signal matters
Across emulsifier groups, fecal short-chain fatty acid concentrations were lower than with placebo. Carboxymethyl cellulose was linked with lower acetate and butyrate, while polysorbate-80 was linked with lower propionate. These metabolites are produced when gut microbes ferment dietary substrates and are part of the conversation between microbes and the intestinal environment.
At the same time, inflammatory markers did not significantly worsen. Fecal calprotectin, C-reactive protein, serum inflammatory proteins, glucose, and insulin were not different during supplementation. Carrageenan increased one measure of intestinal permeability compared with baseline, but this exploratory trial was not evidence that every emulsifier causes a leaky gut.
If packaged foods make up a large share of your diet, use a small food notebook for one week and record products rather than obsessing over individual ingredients. Patterns are more useful than a blacklist.
Do not turn one trial into an ingredient panic
The study does not justify treating soy lecithin, carrageenan, or every emulsifier as poison. The participants were healthy, the intervention was short, and the metabolic changes did not translate into measurable systemic inflammation during the trial.
What it does justify is more attention to overall exposure. A diet built mostly from minimally processed foods naturally reduces the number and variety of additives without requiring you to memorize chemistry.
Glass food storage containers can make leftovers easier to use, and a reusable bottle can reduce reliance on packaged drinks. Neither is a gut treatment. They simply make a lower-additive eating pattern easier.
The Livium recipe
Tool. Read ingredient lists when two otherwise similar foods are easy to compare. Do not spend 20 minutes auditing every grocery item.
Behavior. Shift the base of the diet toward foods that do not need emulsifiers: vegetables, fruit, grains, beans, nuts, eggs, fish, meat, and plain dairy or alternatives that work for you.
Threshold. If you have inflammatory bowel disease, do not use this study to remove large food groups without your gastroenterology team. The trial was conducted in healthy adults and does not establish an IBD treatment.
What progress looks like
Progress is not an emulsifier-free pantry. It is a diet in which packaged convenience foods are supporting players instead of the entire structure.
If you want to compare symptoms, keep the rest of your routine stable for two weeks. A simple kitchen timer can help with batch cooking if time is the barrier. Track abdominal symptoms, stool pattern, and overall diet quality rather than expecting to feel an immediate effect from removing one additive.
| Trial finding | What changed | What did not clearly change |
|---|---|---|
| Short-chain fatty acids | Lower with emulsifier exposure | Does not prove clinical harm |
| Inflammation | No significant increase | Calprotectin and CRP unchanged |
| Permeability | Carrageenan increased one measure | Not universal across emulsifiers |
| Metabolic markers | No major supplementation effect | Glucose and insulin unchanged |
Source: Wellens et al., Clinical Gastroenterology and Hepatology, 2026.
What this changes at the grocery store
The useful shopping question is not whether a package contains one scary-sounding word. It is how often your day depends on foods engineered to stay creamy, stable, or shelf-ready for long periods. A single condiment with lecithin is a different exposure pattern from a diet dominated by packaged snacks, frozen desserts, sauces, bars, and ready meals.
That distinction also keeps the advice realistic. Convenience food can be useful, especially when time, disability, cost, or access limits cooking. The goal is not purity. It is creating enough minimally processed anchors in the week that one additive does not become the entire gut-health conversation.
Future trials need to tell us whether the short-chain fatty acid changes persist, whether they matter clinically, and whether certain people are more susceptible. Until then, the human evidence supports curiosity and moderation more strongly than fear.
Keep the interpretation proportional
The trial is valuable because it moves the emulsifier debate into humans, but it is still an early controlled experiment. A metabolite change is a biological signal, not a diagnosis. The next step is learning whether repeated real-world exposure changes symptoms or disease risk in meaningful ways.
For now, the strongest diet advice remains broader than any one additive: eat a varied diet with enough plant foods and use highly processed foods as conveniences rather than the foundation of every meal.
Plan of action
- Choose one heavily processed daily food and compare simpler alternatives.
- Do not create a universal emulsifier blacklist from one exploratory trial.
- Build meals around minimally processed foods when practical.
- If you have IBD or persistent symptoms, make dietary changes with appropriate clinical guidance.
Table of Content

Know your body better.
Trusted By Thousands Daily





FAQs
Do emulsifiers cause gut inflammation?
This 2026 trial did not find significant increases in the measured intestinal or systemic inflammatory markers.
Should I avoid every food with an emulsifier?
No. The evidence does not support treating every emulsifier or every exposure as harmful.
What are short-chain fatty acids?
They are microbial metabolites produced largely from fermentation in the gut and are involved in intestinal and metabolic signaling.
Legal Disclaimer
The content published on Livium Health is for informational and educational purposes only. Nothing on this site constitutes medical advice, diagnosis, or treatment. Always consult a qualified healthcare provider before making decisions about your health, including changes to medications, supplements, diet, or exercise.
Livium Health is not a medical practice and does not have a patient-provider relationship with its readers. We do not sell supplements, medications, or treatments, and we have no financial relationship with the products or services we reference.
While we work to ensure the information we publish is accurate and up to date, health and medical guidance evolves. We make no guarantees about the completeness or currency of any content on this site. Reliance on any information provided by Livium Health is solely at your own risk.
If you are experiencing a medical emergency, call 911 or your local emergency services immediately.
We may receive compensation, free products, or affiliate commissions for products mentioned in this post. Opinions are our own.